Entry · Ref MTWGJL4M
Dental Crowns Explained: Types, Benefits, and Costs
- Posted
- 2026-11-04
- Last amended
- 2026-11-04
- Account
- @trentonafxj283


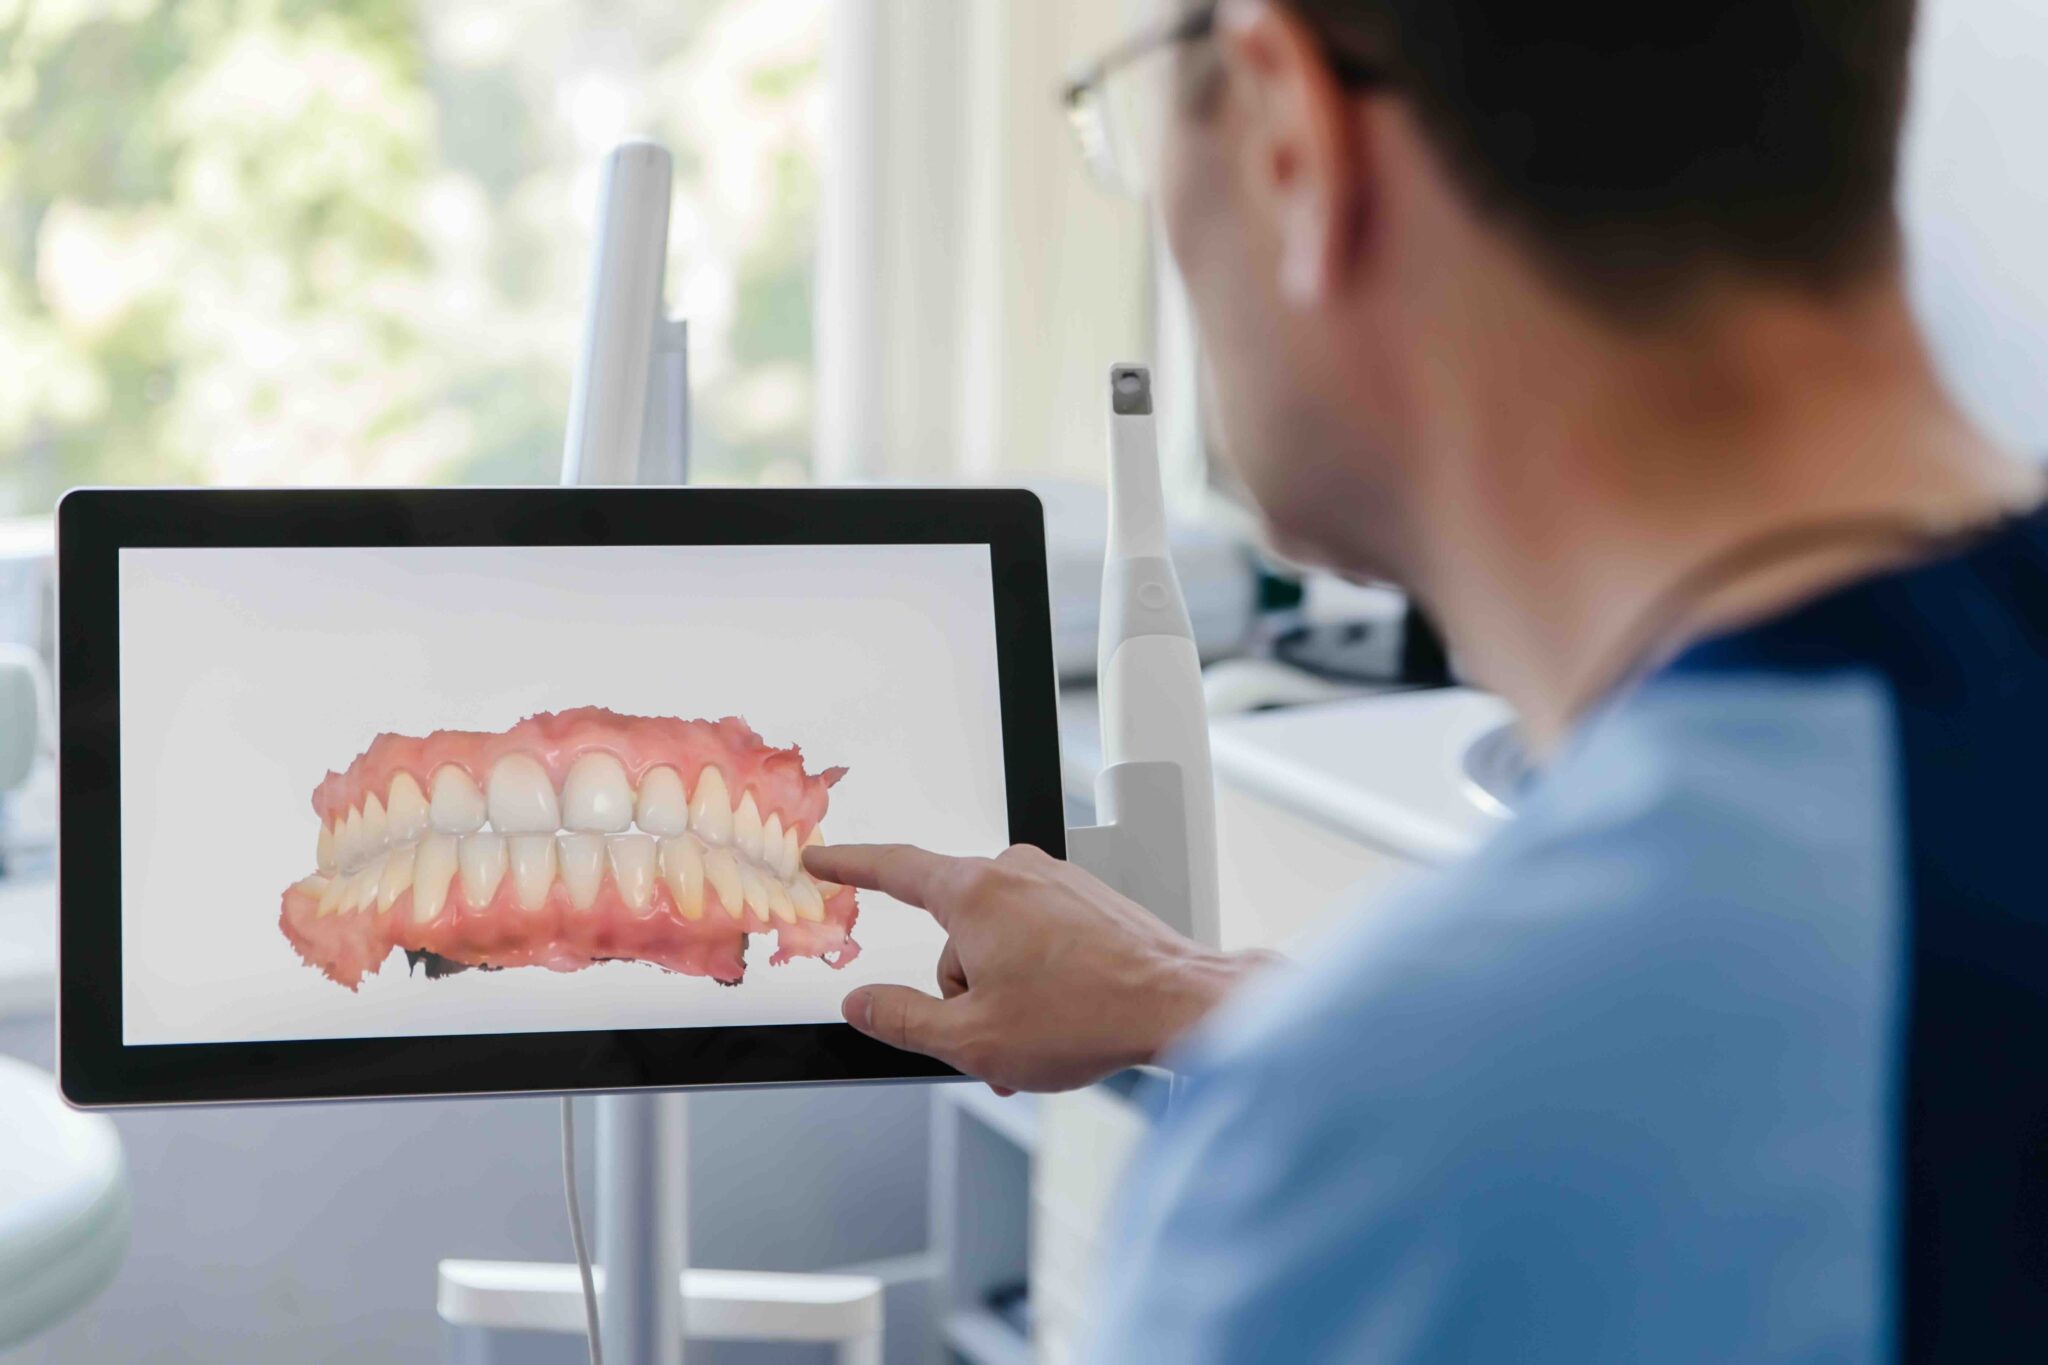
A dental crown is one of those treatments many people have heard of long before they need one. The term sounds straightforward, yet there is a lot packed into it. A crown is not a decorative add-on and it is not limited to cosmetic dentistry. It is a full-coverage restoration that fits over a damaged, weakened, heavily filled, or root canal treated tooth to restore shape, strength, and function. In everyday practice, crowns sit at the intersection of repair and protection. They can save a tooth that would otherwise keep cracking, breaking down, or becoming painful to chew on.
Patients often picture crowns as a last resort before losing a tooth, but that is not quite right. In many cases, a crown is what helps avoid extraction. At the same time, not every damaged tooth needs one. Good treatment planning depends on how much healthy tooth structure remains, whether the tooth has had previous work, where it sits in the mouth, and how much bite force it has to handle. A front tooth with a small chip is a very different case from a molar with a deep old filling and a hairline fracture.
Understanding dental crowns helps people make better decisions because the options differ in material, lifespan, appearance, and cost. A patient choosing a crown is not just buying a product. They are choosing how a tooth will function for years, what it will look like, and how much maintenance it may need.
What a dental crown actually does
A crown covers the visible part of the tooth above the gumline, though in some cases the edge may extend slightly below the gum to create a proper seal and hold. Its job is to act like a protective outer shell. The dentist reshapes the tooth so the crown can fit over it, then bonds or cements the crown in place.
This becomes important when a tooth is too compromised for a regular filling to do the job reliably. A filling replaces missing material in part of a tooth. A crown wraps around the entire prepared tooth. That difference matters most when a tooth has lost a lot of structure. Think of an old molar with a filling that takes up half or more of the chewing surface. Every time that person bites into toast, nuts, or a crusty piece of bread, stress concentrates on the remaining thin tooth walls. Over time, those walls flex and can fracture. A properly designed crown redistributes force more evenly.
Crowns also play a central role in other treatments. They are often used after root canal therapy because those teeth can become more brittle and are more prone to fracture, especially back teeth. They are used to support dental bridges. They are placed on top of dental implants. They can also improve a tooth’s shape or color when simpler cosmetic options are not suitable.
When a crown is recommended
The most common reasons for a crown are practical rather than cosmetic. If a tooth has a very large filling, repeated decay around older restorations, a crack, severe wear, or significant breakage, the dentist may recommend a crown because the tooth needs reinforcement. Sometimes the need becomes obvious after an emergency, such as biting something hard and losing a chunk of a molar. Other times it appears on an X-ray or during routine examination, when the filling-to-tooth ratio has become unfavorable.
There is a judgment call involved. A tooth does not move from “healthy” to “needs crown” at a precise universal threshold. Dentists look at the amount of remaining enamel and dentin, the direction of chewing forces, whether the patient grinds their teeth, and whether the tooth has symptoms. A younger patient with thick tooth structure and no grinding habit may do well with a large bonded filling for years. A patient who clenches at night, has visible wear facets, and has a deep old silver filling on a molar may be much safer with a crown.
Crowns are also common after root canals, particularly on molars and premolars. That recommendation can surprise patients because the pain may be gone once the root canal is complete. The issue then is not infection, but structural survival. The tooth may no longer hurt, yet it may be at risk of splitting if left unprotected.
The main types of dental crowns
The type of crown matters because no single material is ideal for every situation. Dentists balance appearance, strength, thickness requirements, bite forces, and budget.
Dental Crowns- All-ceramic or all-porcelain crowns are chosen when appearance is a priority, especially for front teeth. They can look very natural because they reflect light in a way that resembles enamel.
- Porcelain-fused-to-metal crowns combine a metal substructure with a tooth-colored outer layer. They have a long history of use, though the porcelain can chip and a dark line may become visible near the gum over time.
- Zirconia crowns are known for strength and have become common for back teeth and many other cases. Modern zirconia can look better than older versions, though some forms are still less lifelike than premium layered ceramics.
- Metal crowns, often gold alloy or other metal blends, remain one of the most durable options for heavy chewing areas. They are highly functional but not tooth-colored, so they are usually limited to less visible teeth.
- Same-day milled crowns refer more to the fabrication process than the material. These can be made from ceramic or similar blocks in one visit if the office has the right equipment, though not every case is a good candidate.
Each material has trade-offs. Front teeth place high demands on shade, translucency, and edge detail, while molars demand fracture resistance. A crown that looks beautiful under soft lighting may not be the best option for someone who clenches hard at night. Likewise, the strongest material is not always the most natural-looking.
A closer look at materials and trade-offs
All-ceramic crowns are often the first choice for visible teeth because they avoid metal and can be matched very closely to adjacent teeth. In the right hands and the right case, they can disappear into a smile. That said, ceramics vary. Some are stronger, some are more translucent, and some require more tooth reduction than others. Cosmetic cases often involve detailed discussions about shade, neighboring tooth color, and whether the patient might want whitening before the crown is made. A common disappointment happens when someone crowns a front tooth and then decides to whiten the rest later. The natural teeth can lighten, but the crown color does not.
Porcelain-fused-to-metal crowns were a standard solution for many years and still have valid uses. They offer reliable support, but aesthetics can become an issue with gum recession or heavy wear. If the porcelain chips, the metal beneath may show through. Many people still have these crowns functioning well after a decade or more, which says a lot about their durability when properly made.
Zirconia has changed the conversation because it offers impressive strength and reasonable aesthetics in a broad range of cases. It is especially useful for molars and for patients with heavier bites. However, strength alone does not settle everything. An overly hard or poorly adjusted crown can contribute to wear on the opposing tooth. Precision matters. The bite must be checked carefully, and the surface finish should be smooth and polished.
Metal crowns deserve more respect than they often get in patient discussions. A gold alloy crown on a back molar can be a superb restoration. It can fit very precisely, wear in a tooth-friendly way, and last a very long time. The reason many patients decline them is obvious: they are visible when laughing or opening wide, and many prefer tooth-colored options.
What getting a crown usually involves
The standard process takes two visits, though same-day systems can shorten that. At the first appointment, the dentist examines the tooth, may take X-rays, removes decay or failing filling material, and shapes the tooth so the crown can fit properly. If not enough tooth remains, a buildup may be needed to create a sound foundation. In some cases, a post is placed inside a root canal treated tooth to help retain the core, though posts do not magically strengthen teeth and are only used when indicated.
Once the tooth is prepared, the dentist takes an impression, either with a digital scanner or traditional impression material. Shade selection is done if the crown will be visible. A temporary crown is then placed while the final one is fabricated in a lab. That temporary matters more than many people realize. It protects the prepared tooth, helps maintain position and gum shape, and gives the patient a preview of general contour and feel.
At the fitting appointment, the temporary is removed and the final crown is tried in. The dentist checks the margins, contacts with neighboring teeth, color if relevant, and bite. Small adjustments are common. When everything is right, the crown is cemented or bonded.
Same-day crowns skip the temporary and second visit in some offices. The tooth is prepared, scanned, designed digitally, and milled on site. For the right patient, this can be very convenient. Still, convenience is not the only metric. Some complex cosmetic cases and some demanding bite situations benefit from a skilled dental lab technician working on the crown outside the office.
Benefits that matter in real life
The clearest benefit of a crown is protection. It can keep a compromised tooth in service for many years and restore comfortable chewing. That alone changes day-to-day life. Patients with cracked or broken molars often describe a pattern of chewing on one side, avoiding crunchy foods, or living with a low level of anxiety at every meal. A good crown can end that cycle.
Function is another major advantage. Teeth need proper anatomy to guide chewing forces and maintain contact with neighboring teeth. A heavily broken-down tooth patched repeatedly with fillings may trap food, feel rough, or develop bite problems. A crown can restore more ideal form and contact.
Aesthetics can be a meaningful benefit too, especially with front teeth. A dark, worn, misshapen, or heavily filled tooth can draw the eye immediately when someone smiles. A well-made crown can improve confidence in a subtle but significant way. The best cosmetic work rarely looks dramatic. It simply stops looking damaged.
Crowns can also support broader dental treatment. They anchor bridges, top implants, and protect teeth that are essential for a stable bite. In full-mouth rehabilitation, crowns may be part of rebuilding worn-down teeth so the patient can chew and speak more comfortably.
Limits, complications, and when a crown is not the best answer
Crowns are valuable, but they are not perfect and they are not indestructible. Teeth under crowns can still develop decay, especially at the margin where crown meets tooth. If oral hygiene is poor or the fit is compromised, bacteria can work their way into vulnerable areas. Patients sometimes assume a crowned tooth is “fixed forever,” then are surprised years later when decay appears underneath.
Sensitivity after crown preparation can happen, particularly if the tooth was already inflamed or if a lot of structure had to be removed. In some cases, a tooth that seemed restorable before treatment later declares itself through lingering pain and ends up needing a root canal. That is frustrating, but it does occur. Dentistry is not engineering on passive materials. Living teeth respond in ways that can only be estimated, not guaranteed.
Crowns can chip, loosen, fracture, or feel high in the bite. A crown that is slightly off may not just feel annoying. It can lead to soreness in the tooth, jaw discomfort, or wear on other teeth. That is why post-cementation adjustments matter and why patients should return if something feels wrong.
There are also times when a crown is not the best option. If a tooth is too deeply fractured, has insufficient sound structure above the gumline, or has poor periodontal support, a crown may not offer a predictable long-term result. In those cases, extraction and replacement may be more realistic than trying to save a tooth at any cost.
What dental crowns cost and why prices vary
Cost is one of the first questions patients ask, and for good reason. A crown can be a significant expense. In many areas, a dental crown may cost anywhere from several hundred to over two thousand dollars per tooth, depending on country, region, office type, materials, and whether additional procedures are needed. In higher-cost urban markets, premium cosmetic work can go beyond that range.
The crown itself is only part of the total. A buildup, root canal, gum treatment, diagnostic imaging, or replacement of a missing wall of the tooth can add to the fee. A simple crown on a moderately damaged tooth is one thing. A root canal treated molar with little structure left is another. It is not unusual for patients to compare two estimates and wonder why one is much higher, only to discover they are not comparing equivalent treatment plans.
Several factors usually influence the final cost:
- the crown material and the level of esthetic customization
- the complexity of the tooth and amount of rebuilding required
- whether a lab fabricates the crown or it is made in-office
- the experience of the clinician and the local cost of practice
- insurance coverage, if any, and the plan’s annual maximums or restrictions
Insurance often helps, but coverage can be partial and subject to waiting periods, frequency limits, or proof that the treatment is medically necessary rather than purely cosmetic. It is common for patients to think insurance will cover most of the bill, then find that the plan pays a percentage based on a capped “allowed amount,” not the office fee. Asking for a pre-treatment estimate can prevent surprises.
The cheapest crown is not always the least expensive over time. If a lower-cost restoration fits poorly, feels wrong, or fails early, the replacement cost and frustration can outweigh the initial savings. On the other hand, a premium material is not automatically better if it is being used in the wrong case. Value comes from suitability, fit, and execution.
How long crowns last
Crowns can last a long time, but longevity depends on much more than the material. Ten to fifteen years is a commonly cited rough expectation, and many crowns exceed that. Some fail earlier, especially in patients with heavy grinding, poor oral hygiene, untreated decay risk, or unstable bites.
The underlying tooth matters as much as the crown itself. A beautifully made crown on a weak foundation may not survive nearly as long as a simpler restoration on a healthier tooth. Margins matter. Bite forces matter. Home care matters. Night grinding matters.
One practical reality is that crowns rarely fail all at once without warning. Often there are hints: food packing, floss catching, recurrent sensitivity, a chipped edge, gum inflammation around the margin, or a crown that no longer feels quite right. Regular checkups and X-rays help catch those issues early.
Caring for a crowned tooth
A crowned tooth should be treated like a natural tooth that still needs protection. The crown itself cannot decay, but the tooth underneath can. Brushing thoroughly at the gumline and cleaning between the teeth is essential. Patients sometimes avoid flossing around a crown because they are afraid of pulling it off. If the crown is properly cemented, normal flossing should not dislodge it.
Bite habits make a difference too. Using teeth to crack nuts, tear packaging, or chew ice is hard on both natural teeth and crowns. Patients who grind or clench at night often do well with a night guard, especially if they already have multiple restorations. That small preventive step can save a great deal of repair later.
If a temporary crown comes off before the final appointment, that should not be ignored. Sometimes it can be re-cemented; sometimes it needs to be remade. Leaving a prepared tooth uncovered for too long can lead to sensitivity, shifting, or difficulty fitting the final crown accurately.
Questions worth asking before you agree to treatment
A crown recommendation should come with a conversation, not just a scheduled procedure. Patients do better when they understand why the crown is being advised and what the alternatives are. Sometimes the answer is clear-cut. Sometimes there is a genuine choice between a large filling, an onlay, or a full crown.
A few questions tend to clarify the situation quickly. Ask what problem the crown is solving right now, not just what it might prevent later. Ask whether the tooth has a crack, how much healthy structure remains, and what material makes the most sense for that location in your mouth. Ask whether a root canal is likely or only a possibility. Ask what happens if you wait six months. A good explanation usually sounds specific. It should relate to your tooth, your bite, and your risks, not just a generic statement that “crowns are stronger.”
An onlay or partial-coverage restoration may be worth discussing in some cases. These conserve more tooth structure than a full crown while still protecting weakened areas. They are not suitable everywhere, but they can be an excellent middle ground when the damage pattern allows it.
The bottom line for choosing wisely
Dental crowns are one of the most dependable ways to restore and protect compromised teeth, but they are not interchangeable commodities. The right crown for one person can be the wrong one for another. A back molar in a heavy grinder, a front tooth in a high-smile patient, and an implant crown all call for different priorities.
The best decisions come from balancing durability, appearance, cost, and the actual condition of the tooth. A sound crown can preserve comfort, chewing ability, and confidence for many years. A poorly planned one can become an expensive detour. If your dentist recommends a crown, it is worth slowing down long enough to understand the diagnosis, the material options, the expected lifespan, and the full cost of treatment. That extra conversation often makes the difference between feeling sold to and feeling well cared for.
Simple Dental Vermont
Address: 8914 S Vermont Ave, Los Angeles, CA 90044
Phone number: +13239493000
FAQ About Dental Crowns
How much do crowns cost per tooth?
In the United States, a single dental crown typically costs between $800 and $2,500 per tooth without insurance. The ultimate out-of-pocket price depends heavily on the crown material, the location of the tooth, and whether you have dental insurance coverage.
What is the downside of crowns on teeth?
The primary downside of a dental crown is that the procedure permanently removes natural tooth enamel to shape the tooth for the cap.
Why do dentists push for crowns?
Dentists recommend crowns because a large filling cannot provide enough strength when a tooth loses a major portion of its structure or faces heavy chewing pressure.